

Primobolan (Methenolone): Clinical Comparison of Injectable Depot vs. Oral Acetate, Cycle Protocols & Endocrine Recovery
Methenolone, universally recognized by its historic trade name Primobolan, stands as one of the most refined dihydrotestosterone (DHT) derivatives in sports pharmacology. Prized for its exceptional nitrogen-retaining properties, zero estrogenic conversion, and remarkably low hepatotoxicity, it remains the gold standard for lean tissue preservation during caloric deficits. This comprehensive guide examines optimal primobolan cycle dosage strategies, pharmacokinetic differences between delivery vectors, synergistic stacking, and evidence-based Post Cycle Therapy. Disclaimer: This content is strictly for educational and harm-reduction purposes and does not constitute medical advice.
1. Pharmacological Profile & Mechanism of Action
Methenolone is a structurally altered derivative of dihydrotestosterone (DHT). Its chemical architecture features a double bond between carbons 1 and 2, which significantly amplifies its anabolic-to-androgenic ratio, alongside an added 1-methyl group that protects the steroid nucleus from rapid hepatic breakdown. Unlike 17-alpha-alkylated oral compounds that exert heavy metabolic stress on liver enzymes, Methenolone offers a uniquely benign safety profile when administered responsibly.
Clinically, Methenolone exhibits a moderate anabolic rating (approximately 88 relative to testosterone) and a distinctly low androgenic rating (roughly 44–57). Its primary physiological benefit lies in its potent ability to enhance nitrogen retention within skeletal muscle tissue and inhibit glucocorticoid (cortisol) catabolism. Because it is a DHT-derived molecule, it cannot interact with the aromatase enzyme. Consequently, athletes experience zero estrogenic side effects—meaning no subcutaneous water retention, no gynecomastia, and no estrogen-induced blood pressure spikes.
Source Pharmaceutical-Grade Primobolan Depot
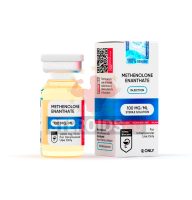
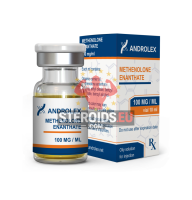
Explore our verified selection of Methenolone Enanthate 100 mg/ml vials and ampoules from Hilma Biocare and Androlex, backed by independent Janoshik HPLC purity reports and shipped discreetly from our EU warehouse.
2. Injectable Methenolone Enanthate vs. Oral Acetate
A critical distinction in cycle planning involves selecting between the intramuscular depot formulation (Methenolone Enanthate) and the oral tablet formulation (Methenolone Acetate). While both deliver the identical active parent hormone—methenolone—their esterification and route of administration dictate vastly different pharmacokinetic behavior and milligram-for-milligram efficiency.
Injectable preparations such as Methenolone Enanthate Hilma Biocare 10ml/100 mg/ml, Primos 100 mg/ml, and Androlex Methenolone Enanthate bypass first-pass hepatic metabolism entirely, offering nearly 100% systemic bioavailability. Conversely, athletes who prefer needle-free administration often turn to Primobolan Tablets, which utilize a 1-methyl group and an acetate ester to survive oral ingestion. Because oral Methenolone lacks C17-alpha alkylation, roughly 40% to 50% of the compound is still degraded by the liver before reaching systemic circulation, necessitating higher daily milligram dosages to match the tissue-building efficacy of the injectable depot.
| Pharmacokinetic Parameter | Primobolan Depot (Methenolone Enanthate) | Oral Primobolan (Methenolone Acetate) |
|---|---|---|
| Administration Route | Deep Intramuscular Injection | Oral Tablet Ingestion |
| Active Half-Life | ~7 to 10.5 Days | ~4 to 6 Hours (Requires split daily dosing) |
| Systemic Bioavailability | Near 100% (No first-pass hepatic loss) | ~50–60% (Partial hepatic degradation) |
| Hepatotoxicity (Liver Stress) | Negligible | Very Low (Non-17aa structure) |
| Standard Dosing Frequency | Twice Weekly (Every 3.5 Days) | 2 to 3 Times Daily |
| Cost-to-Efficacy Ratio | High (Optimal serum stability) | Moderate (Requires higher daily mg intake) |
3. Optimal Primobolan Cycle Dosage Protocols
Determining the ideal primobolan cycle dosage depends heavily on biological sex, training maturity, and whether the compound is deployed as a primary anabolic builder or as an estrogen-modulating secondary agent. Because Methenolone acts slowly and steadily by accruing dry, contractile myofibrillar tissue rather than intracellular glycogen bloat, cycle durations using the Enanthate ester should span a minimum of 10 to 16 weeks.
Many novice athletes research a primobolan only cycle dosage hoping to avoid injections or testosterone-related side effects. While female competitors can successfully execute a standalone Methenolone cycle at micro-doses (25–50 mg/week injectable or 10–25 mg/day oral), men running a solo Primobolan protocol at effective physique-enhancing doses (400+ mg/week) will experience significant hypothalamic-pituitary-testicular axis (HPTA) suppression. Without an exogenous base of Testosterone Enanthate, male users risk crashing their endogenous estradiol (E2) and DHT levels, leading to lethargy, joint dryness, and diminished libido.
| User Tier & Experience | Injectable Enanthate Dosage | Oral Acetate Dosage | Recommended Cycle Length | Primary Clinical Objective |
|---|---|---|---|---|
| Beginner (Male) | 300 – 400 mg / week | 75 – 100 mg / day | 10 – 12 Weeks | Lean mass preservation, mild recomposition, minimal side effects |
| Intermediate (Male) | 500 – 600 mg / week | 100 – 150 mg / day | 12 – 16 Weeks | Noticeable muscle density, vascularity, nitrogen retention in deficit |
| Experienced (Male) | 600 – 800 mg / week | 150 – 200 mg / day | 14 – 16 Weeks | Contest preparation, maximum cosmetic hardness & E2 modulation |
| Female Athletes | 50 – 100 mg / week | 10 – 25 mg / day | 6 – 8 Weeks | Safe lean tissue accrual with low virilization risk |
4. Synergistic Cutting & Recomposition Stacks
Primobolan truly shines when integrated into multi-compound protocols. Because it does not compete aggressively for the aromatase enzyme or elevate prolactin, it pairs seamlessly with a base of testosterone and non-aromatizing oral finishers. When designing comprehensive Steroid Cycles, pairing Methenolone Enanthate with long-ester testosterone allows both compounds to follow an identical twice-weekly injection cadence.
The Classic Golden-Era Recomp
Testosterone Enanthate (300 mg/wk) + Primobolan Depot (400–500 mg/wk) for 12–14 Weeks. This foundational ratio keeps serum estradiol perfectly balanced without needing harsh aromatase inhibitors, delivering steady, keepable lean tissue gains and enhanced recovery.
Aesthetic Summer Cutting Stack
Testosterone Propionate (150 mg/wk) + Primobolan Depot (500 mg/wk) + Oral Finisher (Weeks 7–12). Ideal for aggressive caloric deficits. Protects catabolic muscle loss while stripping subcutaneous adipose tissue, yielding granite-like muscle separation.
Advanced Contest Prep Protocol
Testosterone Base (200 mg/wk) + Primobolan (600 mg/wk) + Trenbolone or Masteron (300 mg/wk). Designed strictly for seasoned physique competitors seeking extreme dryness, striated cosmetic detail, and maximal androgen receptor saturation.
Peptide & GH Synergy Stack
TRT Testosterone (150 mg/wk) + Primobolan (400 mg/wk) + Somatropin (2–4 IU/day). Combining Methenolone with growth hormone creates profound lipolytic synergy and collagen synthesis without fluid retention or insulin resistance spikes.
For athletes looking to polish their physique during the final 6 weeks of a cutting phase, adding Anavar at 30–50 mg per day alongside injectable Primobolan amplifies phosphocreatine synthesis and visceral fat oxidation while keeping hepatic transaminases well within manageable parameters. Similarly, incorporating pharmaceutical HGH (Somatropin) elevates systemic IGF-1 levels, creating an anabolic environment where Primobolan can drive hyper-efficient protein synthesis.
5. Side-Effect Management & Required Bloodwork
Although Methenolone is universally regarded as one of the safest anabolic-androgenic steroids ever synthesized, it is not entirely devoid of physiological trade-offs. Proactive harm reduction requires understanding its impact on cardiovascular biomarkers, hair follicles, and endocrine feedback loops.
- Cardiovascular & Lipid Alteration: Like all DHT derivatives, Primobolan suppresses High-Density Lipoprotein (HDL) and can mildly elevate Low-Density Lipoprotein (LDL) via hepatic lipase stimulation. Supplementing daily with 4g of high-EPA/DHA Omega-3 fish oil, Citrus Bergamot (1000 mg/day), and regular Zone-2 cardiovascular training is strongly advised.
- Androgenic Alopecia (Hair Loss): Because Methenolone is already a DHT derivative, 5-alpha-reductase inhibitors (such as Finasteride or Dutasteride) are completely ineffective at preventing Primobolan-related hair thinning. Individuals genetically predisposed to male pattern baldness should utilize topical ketoconazole shampoos and topical androgen receptor antagonists (e.g., RU58841).
- Estrogen Depletion (Low E2): Because Primobolan exhibits intrinsic anti-aromatase activity, running a high Primobolan-to-Testosterone ratio (e.g., 600 mg Primo with only 150 mg Testosterone) can inadvertently crash serum estradiol. Always confirm your E2 levels via bloodwork before taking any ancillary AI.
- Hormone Panel: Total & Free Testosterone, Sensitive Estradiol (E2), LH, FSH, and SHBG.
- Cardiovascular & Lipid Panel: Total Cholesterol, HDL, LDL, Triglycerides, and ApoB.
- Hematology & Organ Function: Complete Blood Count (CBC with Hematocrit/Hemoglobin), CMP (ALT, AST, GGT, Bilirubin), and Cystatin-C for accurate renal filtration assessment.
6. Post Cycle Therapy (PCT) & HPTA Recovery
Following the conclusion of any Methenolone cycle, exogenous androgens will have suppressed endogenous gonadotropin-releasing hormone (GnRH), Luteinizing Hormone (LH), and Follicle-Stimulating Hormone (FSH). Executing a structured Post Cycle Therapy protocol is mandatory if you are not transitioning back to a medical Testosterone Replacement Therapy (TRT) cruise.
Timing your PCT depends entirely on the ester used. If you ran Oral Methenolone Acetate, SERM therapy begins 24 to 48 hours after your final tablet. If you utilized injectable Methenolone Enanthate (such as Hilma Biocare or Primos 100 mg/ml), you must wait 14 to 18 days after your final injection to allow supraphysiological blood concentrations to clear before initiating recovery agents.
- Weeks 1–2 (Clearance Bridge): Administer HCG (Gonadotropin) at 500 IU every other day during the two-week ester clearance window to reverse testicular atrophy and prime the Leydig cells prior to SERM introduction.
- Weeks 3–6 (SERM Restoration): Utilize Nolvadex (Tamoxifen Citrate) at 20 mg/day for 4 weeks. For longer 16-week cycles, stack Clomid (Clomiphene Citrate) at 25–50 mg/day alongside Tamoxifen for the first two weeks to robustly stimulate pituitary gonadotropin secretion.
7. Frequently Asked Questions (FAQ)
What is the recommended primobolan only cycle dosage?
For female athletes, an effective and safe primobolan only cycle dosage is 10–25 mg per day of oral Methenolone Acetate or 50–75 mg per week of injectable Methenolone Enanthate for 6–8 weeks. For male users, a solo cycle is generally discouraged due to HPTA suppression and low estradiol risks; however, if conducted, men typically require 400–600 mg/week injectable or 100–150 mg/day oral for 10–12 weeks, ideally paired with at least a TRT base of testosterone.
Does Primobolan cause water retention or gynecomastia?
No. Because Methenolone is a dihydrotestosterone (DHT) derivative with a modified A-ring, it is chemically incapable of interacting with the aromatase enzyme. It produces zero estrogen conversion, ensuring all muscular gains are completely dry, lean, and free of subcutaneous edema or gynecomastia risk.
How long does it take to see results from Methenolone Enanthate?
Because the Enanthate ester releases slowly into systemic circulation, initial visual changes—such as enhanced muscular fullness, vascularity, and improved recovery—typically become noticeable between weeks 4 and 5. Peak nitrogen retention and cosmetic hardening occur between weeks 8 and 14.
Is Oral Primobolan liver toxic like Dianabol or Winstrol?
No. Unlike Dianabol, Winstrol, or Anadrol, Oral Primobolan (Methenolone Acetate) is not C17-alpha-alkylated. Instead, it utilizes a 1-methyl group for oral bioavailability, making its impact on hepatic transaminases (ALT/AST) exceptionally mild compared to traditional oral steroids.
Why does Primobolan lower estrogen during a Testosterone cycle?
Methenolone and its metabolites act as competitive inhibitors of the aromatase enzyme. When stacked alongside Testosterone, Primobolan occupies aromatase binding sites without converting to estrogen, effectively lowering serum estradiol levels naturally. A 1:1 or 5:4 ratio of Testosterone to Primobolan is often ideal to keep estradiol in the healthy mid-normal range.
Can I mix Primobolan Depot and Testosterone Enanthate in the same syringe?
Yes. Both Methenolone Enanthate (e.g., Hilma Biocare or Androlex 100 mg/ml) and Testosterone Enanthate are oil-based depot solutions. They can be safely drawn into the same syringe for a single combined intramuscular injection twice per week.


Write a comment